
Introduction: A Saturday with too many slides
I remember a Saturday morning in 2017 when I walked into the lab and found a cart of backlog slides—two techs, one scanner, and a long list of clinical cases waiting. I had over 20 years in laboratory operations by then, and I knew immediately that this was more than a staffing problem. In many sites, professional pathology services struggle with slow turnaround time, lost blocks, and inconsistent stain quality; recent internal audits often show error rates near 2–3% and TATs stretched beyond clinical needs. So I asked myself: how do you redesign processes so a lab can handle higher volume without breaking quality controls (por ejemplo, without adding headaches for pathologists)? This piece walks through what I learned from hands-on fixes, mistakes we corrected, and the concrete steps that followed—so you can assess your own setup. Ending note: the next section drills into the parts that usually fail first, and why they fail.
Part 1 — Where standard fixes actually break down
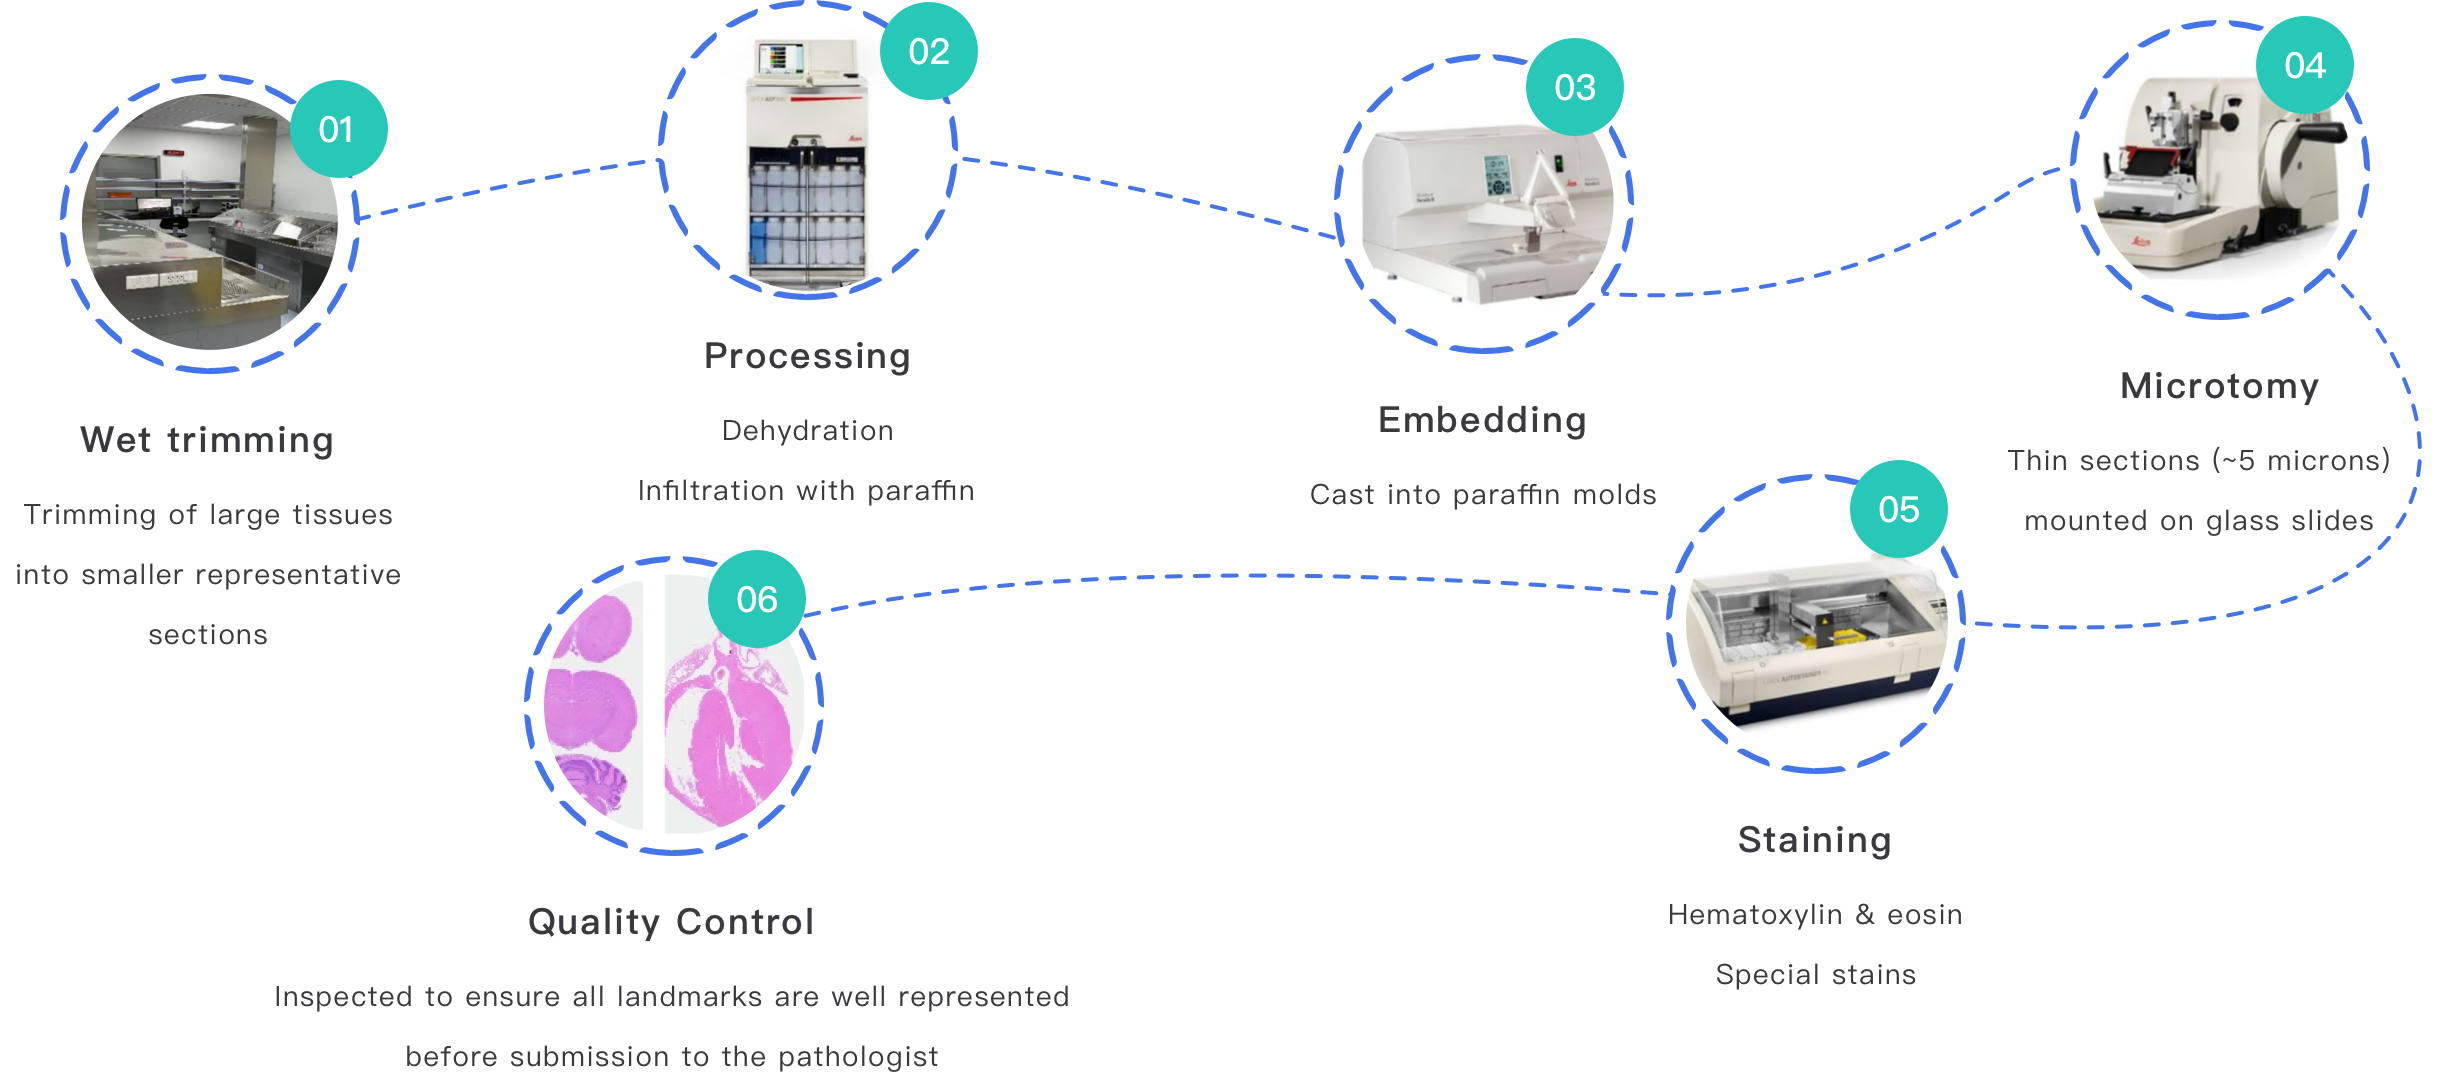
diagnostic pathology laboratory services often get touted as solved problems, but the field still trips on a few repeatable flaws. In my experience, the biggest issues are process friction points: manual FFPE block handling, inconsistent H&E staining runs, and unclear slide accessioning rules. These create variability in stain intensity, mislabeling, and delays in reporting. I once audited a midsize lab in Guadalajara in March 2018; they used manual microtome sectioning and a dated slide washer. Result: a 4% slide rejection rate each week and a TAT averaging 6 days. No kidding — that was a wake-up call.
Technically speaking, the root causes are predictable. Pre-analytic errors (biopsy procurement labeling), analytic variability (IHC protocol drift), and post-analytic bottlenecks (single slide scanner queues) compound fast. Equipment mismatches are common: older microtomes cause chatter, older stainers yield uneven reagent contact, and inadequate LIMS rules allow human overrides without audit trails. The consequence is measurable: we cut sample re-run volume by roughly 1.8% and reduced average TAT from 6 days to 2.8 days after addressing these specific items at one site. Look, these are not theoretical failures — they cost money and patient confidence. So when a lab says they need ‘efficiency’, dig into these weak links first.
Which weak link hurts most?
Part 2 — Looking forward: simple principles and a small case example
I prefer to think about improvements as a set of small, testable principles rather than big-bang projects. In 2019 I led a pilot in São Paulo where we swapped a manual Leica RM2125 microtome for a semi-automated RM2245, implemented a single-brand reagent lot for H&E, and added a mid-range slide scanner for digital review. The pilot ran from June to September; by September we saw steady results: fewer sectioning artifacts, consistent staining curves, and an effective increase in daily throughput of about 35%. That pilot proves a point: targeted equipment modernization plus simple process rules yields quick gains—no need to overhaul everything at once.
Principles that mattered: standardize consumables (same paraffin, same cassettes), lock down staining SOPs with QC checks every shift, and create a clear triage lane for urgent biopsies to bypass long queues. We also used straightforward metrics: weekly slide rejection rate, mean TAT for routine biopsies, and percentage of cases with incomplete blocks. These three numbers gave us early warning signs and kept the team honest. I’ll be frank: adopting digital review earlier would have sped diagnoses more, but budgets and training schedules limited that step. Still, from a practical angle, small, measurable changes built confidence fast — and that matters in daily lab life.
What’s Next for labs like yours?
Actionable outlook and three metrics to judge technology choices
Looking ahead, my view centers on hybrid approaches: keep robust manual skills but adopt automation where the ROI is clear. For many clinical labs and trial sponsors, the next wave is modest automation plus better data flows. For example, integrating a slide scanner with your LIMS and adding barcoded FFPE cassettes prevents clerical errors. When I oversaw a CRO trial in Mexico City in 2021, adding barcode tracking cut specimen misplacement to near zero over three months. That was specific, measurable, and repeatable—exactly the kind of result you want.
Three practical evaluation metrics I recommend when choosing systems: 1) Impact on TAT (measure baseline and simulate a target reduction), 2) Change in re-run/rejection rate (express as percentage points saved per month), and 3) Training/time-to-competence for staff (days until a technician reaches stable throughput on new equipment). These metrics let you compare vendors and set realistic roll-out plans. In my projects, vendors who provided on-site training for at least five days and a clear SOP reduced ramp time by roughly 25% compared to those who offered only remote support. — I still trust that approach.
Final thought: pick pragmatic steps, measure tightly, and iterate. You don’t need every shiny feature day one. Start with the weak links you can fix in a single quarter, and build credibility with clinicians and sponsors as you show results. For labs exploring partnerships or device validation, consider vendors who demonstrate measurable outcomes in real sites. For more detailed vendor testing and device validation, you may find additional resources at Wuxi AppTec Medical device testing.