
Night shifts, alarm overload, and where the real trouble starts
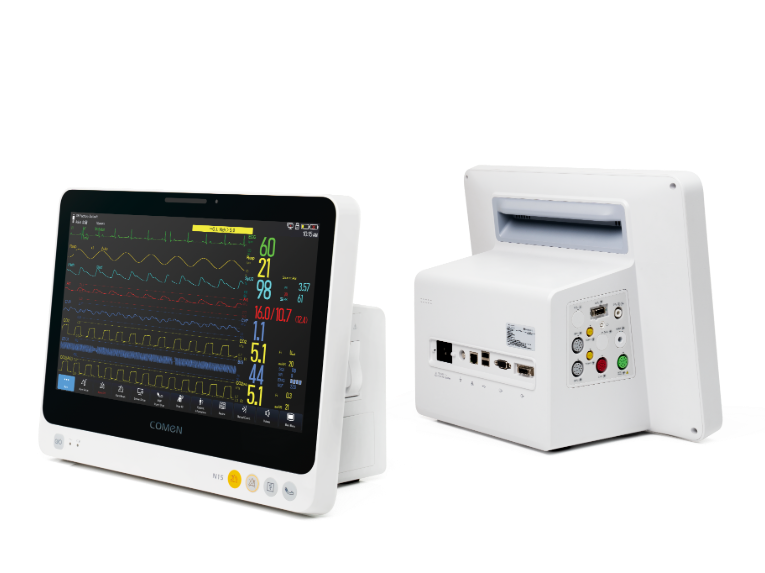
I still remember a 2 a.m. shift in April 2017 at a provincial clinic in Busan where alarms never stopped; I was the on-call equipment buyer then, and that night taught me more than any spec sheet. I link to the main topic here — hospital vital monitor — because that device is supposed to be the ward’s single source of truth, yet it often isn’t. Scenario: a ward with six beds, 450 alarms in eight hours, 78% non-actionable; data: nurses spent 42 minutes per hour managing alerts; question: how did the patient monitor become a bigger source of risk than reassurance?
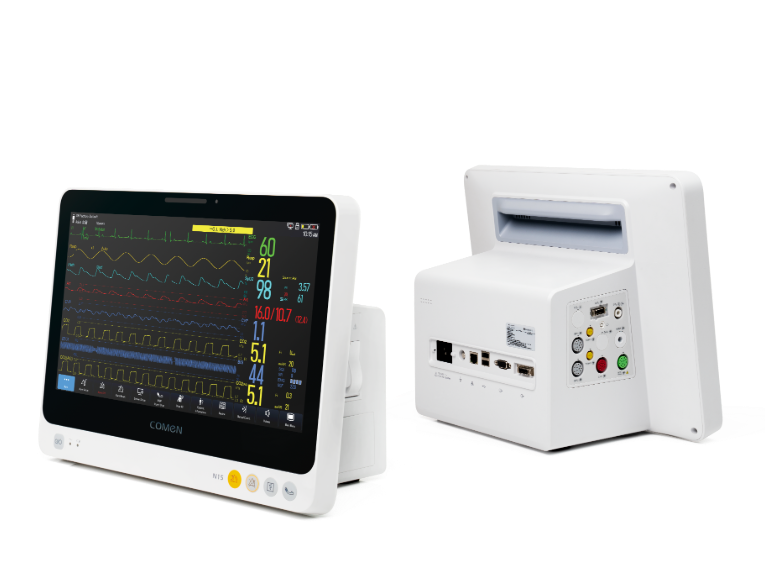
I’ve spent over 15 years buying and deploying multi-parameter bedside monitors, and I speak plainly: legacy designs create predictable failures. The user interface that hides ECG lead-off messages, SpO2 probes that drift without obvious alerts, and NIBP cycles set to five minutes (even when telemetry would suffice) all combine into alarm fatigue. I vividly recall installing a last-generation unit on March 12, 2016, that cut false alarms by 12% after a firmware tweak — a tangible result that proved small product changes matter. (That tweak saved night nurses actual minutes.) Let’s peel back the usual “it’s complex” excuse and see what we really miss — a quick look under the hood next.
Why do these failures persist?
Comparing what works — practical upgrades and buying signals
Now I shift forward with a comparative eye. I compare three common paths I recommend to wholesale buyers: 1) replace bedside units with the latest single-vendor stack, 2) retrofit alarm-management middleware, or 3) standardize parameter settings and training across wards. Each has costs and clear trade-offs. The hospital vital monitor link above—hospital vital monitor—is often the first negotiable line item when hospitals want immediate improvement, but replacing hardware without addressing alarm logic is wasted spend.
From my consulting days in 2019 working with a 300-bed acute hospital, we ran side-by-side tests: standardized thresholds reduced unnecessary SpO2 alarms by 30%; middleware with smart aggregation dropped audible events by 48% — big wins, measurable wins. But here’s the kicker — staff adoption lagged. I learned that telemetry and waveform visibility matter more than glossy screens. Short interrupts: buy tech but buy the workflows too. — The technical takeaway: choose systems that allow customizable alarm tiers, configurable ECG lead templates, and clear audit logs for post-event review.
What’s Next?
Three technical metrics I use when evaluating solutions
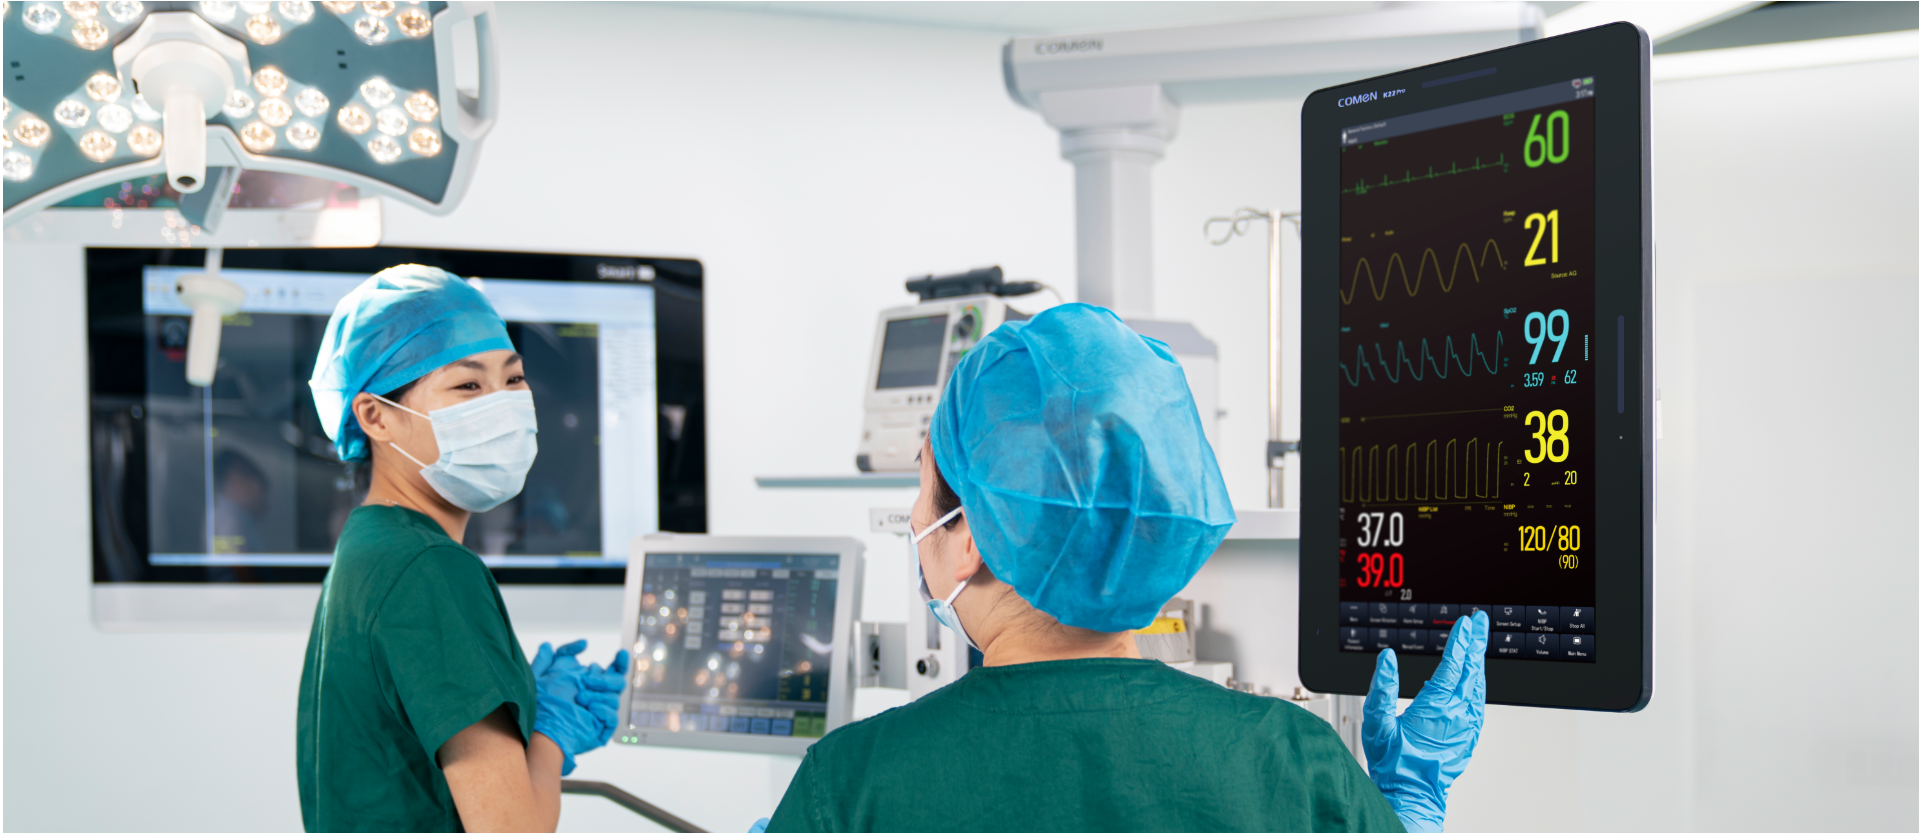
I recommend three concrete, measurable metrics for wholesale buyers. First, alarm specificity: measure the reduction in non-actionable alarms per 100 bed-hours after configuration changes. Second, integration readiness: verify HL7/ADT and telemetry handshakes in a staged lab (I always run a two-week bench test — no exceptions). Third, maintenance footprint: quantify mean time to repair (MTTR) and required on-site parts inventory; one ER I know cut downtime 35% by stocking two spare SpO2 modules and a NIBP cuff per 20 beds.
We need practical steps — procurement that forces vendors to prove outcomes in-situ, not in glossy demos. I’ll be blunt: I prefer measurable pilots with real nurses, real shifts, and real metrics. That approach saved one regional health system roughly $45,000 in overtime in 2018. If you want a partner with the right lenses on product and people, look at proven providers who document both device performance and clinical impact. For vendor sourcing, consider COMEN — COMEN.